



 Inglês (pdf)
 Artigo em XML
 Referências do artigo

 Tradução automática
 Enviar este artigo por email
 Citado por SciELO
 Citado por Google
 Similares em
SciELO
 Similares em Google

 Permalink


INTRODUCTION
The World Health Organization (WHO) has declared that smoking is a public health problem; this habit became popular in the last century and still persists today, smoking tobacco causes chemical and psychological addiction and can cause physiological changes 1. Thus, nicotine is one of the substances found in tobacco, producing addiction and significantly affecting the central nervous system, which is one of the most complex and important systems of the human body 2,3. Therefore, tobacco smoking damages most of the organs and systems of the body, decreasing the overall health of the person, as well as causing cancer of the lung, esophagus, larynx, mouth, kidney, liver, stomach, among others; as well as respiratory tract infections, COPD, chronic bronchitis and pneumonia 4,5.
Among the physiological changes caused by tobacco consumption are vocal alterations 6 and dysphonia, which is an alteration in vocal quality, where not only the acoustic qualities of the voice are affected, such as intensity, tone, timbre and duration, but also the anatomical part of the phonatory apparatus, causing an altered oral communication 7,8. Consequently, people suffering from dysphonia and voice disorders are more prone to develop social and communication problems, causing a decrease in the quality of life and in their physical and/or mental state 7,9,10.
On the other hand, COPD is mainly caused by tobacco consumption 11,12,13, and is defined as a common respiratory condition, which is mainly characterized by airflow limitation 7, this limitation hinders the process of expelling air from the lungs, which triggers difficulties to breathe properly 14,15. Dysphonia is a common finding in COPD 11,16, as constant coughing is a common symptom of this pathology, it can cause incomplete adduction of the vocal cords triggered by vocal fatigue, and it is usually perceived as shortness of breath 7.
Additionally, COPD can affect voice production directly, associated with respiratory impairment and decreased lung volume 17, and, indirectly, as a side effect of medication and associated with concurrent symptoms 16 18. According to the American Speech-Language-Hearing Association, COPD symptoms such as shortness of breath, constant cough, and mucous, can cause alterations in the larynx and vocal cords causing voice problems 17.
In this context, people with COPD have a significantly higher rate of dysphonia 11,19; not only because of poor respiratory support, but also because of the use of inhaled corticosteroids (ICS) 16, symptoms associated with these diseases, such as cough, history of previous or current smoking, and common comorbidities of lung disease 11,20.
COPD is one of the 10 leading causes of morbidity and mortality in the adult population worldwide 21,22, its global prevalence is 11.4% in people aged 30 years or more 23; in Europe it has a prevalence of 9%, 11% in Latin America, 14.1% in North America, 8.6% in Japan, 10% in Asia, and 6% in the United States 24,25. In Mexico, it is also one of the 10 leading causes of morbidity and mortality; a review study found that 54-77% of patients with COPD of moderate severity were tobacco smokers, while 38-51% of those with very severe stages of the disease also smoked 2,26.
Similarly, the epidemiology of voice disorders among the general population is variable and has a high recurrence rate, approximately, 30% of adults have experienced a voice disorder during their lifetime and almost 7% report a current voice problem 27,28; in Sweden, 16.9% of adults experience a voice disorder, and 21.9% of adults in the United States also experience a voice disorder at some point in their lives 7,29,30. Likewise, the World Health Organization (WHO) reported that tobacco smoking causes the death of more than 5 million people each year and 70% of COPD deaths have smoking in common 2,31,32.
In accordance with the above and considering the arguments and findings previously revealed, the present paper aims to conduct a systematic review of the literature, thus, the following research question arises: Does smoking produce Organic Dysphonia in adults with COPD?
MATERIALS AND METHOD
This review was conducted following the parameters proposed by the PRISMA statement, a tool that allowed the systematic review of the scientific literature based on the search and selection of research articles, providing updated guidance on the presentation of systematic reviews 33,34,35. To this end, the databases were initially identified and the key terms in the search for information were defined. The studies were selected on the basis of inclusion and exclusion criteria, which facilitated the evaluation of their quality and reliability and thus made it possible to answer the research question posed.
The PICO model was used to construct the research question, which constitutes a specialized format to develop the clinical question, describing the components that integrate it, allowing to improve the specificity and conceptual clarity of the clinical problems to be studied, as well as allowing the searches to have a higher quality and precision, which allows to collect pertinent and precise data to answer the problem question 36,37.
The classification of the quality of the evidence and grading of the strength of recommendation was performed through the GRADE system; this system is highly specialized for the scientific analysis of the most relevant studies for the present research 38,39. It is a web application for creating managing and sharing summaries of research evidence (called evidence profiles and summary of results table), such tables are often used to summarize evidence from systematic reviews, these tables present key information about the relevant outcomes for a given measured care question, such as the body of evidence, judgments about the underlying quality of evidence, key statistical findings, and a rating for the quality of evidence for each outcome 40,41.
Research Question
In accordance with the topic posed for the research, the components of the PICO model shown in table 1 were established, resulting in the following research question: Does smoking produce Organic Dysphonia in adults with COPD?
Inclusion and Exclusion Criteria
Table 2 Inclusion and Exclusion Criteria
| Inclusion Criteria | Exclusion Criteria |
|---|---|
| Articles where subjects with COPD are found. | Articles where no subjects with COPD are present |
| Articles related to Smoking as a cause of Organic Dysphonia in adults with COPD | Articles unrelated to smoking as a cause of Organic Dysphonia in adults with COPD. |
| Full text articles | Articles without full text |
| Articles with a 10-year publication time window | Articles with a publication time window of more than 10 years |
| Articles | Literature such as these, research reports and projects, working papers, newsletters, technical reports, technical recommendations and standards, books, abstracts, academic courses and lecture notes. |
Source: own elaboration.
Sources of Information
Key terms were selected from the Descriptors in Health Sciences (DESC) and Medical Subject Headings (MESH) (see table 3).
Table 3 DESC and MESH Descriptors
| Source | Keyword | Related terms |
|---|---|---|
| DESC MESH | Dysphonia | Spastic Dysphonia, Phonation disorders |
| DESC MESH | Vocal Cord Dysfunction | No records found |
| DESC MESH | Voice | No records found |
| DESC MESH | Phonation | No records found |
| DESC MESH | Vocal Cords | True Vocal Cord, Vocal cords, vocal ligaments, vocal fold |
| DESC MESH | Voice Quality | No records found |
| DESC MESH | Voice Disorders | No records found |
| DESC MESH | Pulmonary Disease, Chronic Obstructive | COAD, COPD, EVOC, Chronic Obstructive Airway Disease, Chronic Obstructive Pulmonary Disease, Chronic Obstructive Lung Disease, Chronic Obstructive Pulmonary Diseases, Chronic Obstructive Pulmonary Disease, Chronic Airflow Obstruction, Chronic Airflow Obstruction |
| DESC MESH | Risk Factors | Health Correlations Risk factor, Social Risk Factors, Populations at Risk, Population at Risk, Risk Factor Scores, Risk Scores |
| DESC MESH | Cigarette Smoking | Smoking cigarette, Cigarette Smoking Habit |
| DESC MESH | Smoking | Smoking Action, Smoking Behavior, Smoking Behaviors, Smoking habit |
| DESC MESH | Nicotine | No records found |
| DESC MESH | Tobacco Smoking | Tobacco Smoking Habit, Smoking Habit, Tobacco habit |
| DESC MESH | Tobacco | Nicotiana, Nicotiana tabacum |
| DESC MESH | Tobacco Use Disorder | Nicotine addiction, Nicotine dependence, Tobacco Unit, Nicotine Use Disorder, Tobacco Use Disorder |
| DESC MESH | Tobacco Products | Bidi, Cigarette, Bidi Cigarettes, Cigars Cigars, Kretek, Kreteks, Cigars, Bidi Tobacco, Kretek Tobacco, Kreteks Tobacco, Pipe tobacco, Túbanos |
Source: Information obtained from DESC and MESH.
Search Strategies
A search strategy was developed with the help of databases, some of which are part of the digital library of the University of Pamplona, Colombia. Subsequently, search equations were designed with the terms found. These equations were created using logical AND/OR operators and symbols such as " and (). The information search was carried out in PUBMED, SPRINGER LINK, SCIENCEDIRECT, SCOPUS and EBSCO, using the English language (see table 4).
Table 4 Search Equations
| Database | Search Algorithm |
|---|---|
| PUBMED, SPRINGER LINK, SCIENCEDIRECT, SCOPUS, y EBSCO | (“Pulmonary disease, chronic obstructive”) AND (“Dysphonia”) AND (“Tobacco”) |
| (“Pulmonary disease, chronic obstructive”) AND (“Vocal Cord Dysfunction”) AND (“Tobacco”) | |
| (“Pulmonary disease, chronic obstructive”) AND (“Dysphonia” OR “Voice”) AND (“Cigarette Smoking” OR “Tobacco”) | |
| (“Dysphonia” OR “Voice Disorders”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco Use Disorder”) | |
| (“Voice Disorders”) AND (“Tobacco Smoking”) AND (“Pulmonary Disease, Chronic Obstructive”) | |
| (“Cigarette Smoking”) AND (“Voice Disorders” OR “Voice Quality”) AND (“Pulmonary Disease, Chronic Obstructive”) | |
| (“Pulmonary disease, chronic obstructive”) AND (“Dysphonia”) AND (“Risk Factors”) AND (“Tobacco”) | |
| (“Pulmonary disease, chronic obstructive”) AND (“Phonation” OR “Vocal Cords”) AND (“Tobacco Smoking” OR “Nicotine”) | |
| (“Pulmonary disease, chronic obstructive”) AND (“Voice Disorders” OR “Voice “) AND (“Smoking” OR “Tobacco Use Disorder”) | |
| PUBMED, SPRINGER LINK, SCIENCEDIRECT, SCOPUS, y EBSCO | (“Dysphonia” OR “Vocal Cord Dysfunction” OR “Voice Disorders”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco Use Disorder” OR “Smoking”) |
| (“Pulmonary disease, chronic obstructive”) AND (“Dysphonia” OR “Voice”) AND (“Cigarette Smoking” OR “Tobacco”) AND (“Risk Factors”) | |
| (“Dysphonia”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Cigarette Smoking”) | |
| (“Vocal Cord Dysfunction” OR “Phonation”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Smoking” OR “Tobacco Smoking”) | |
| (“Voice” OR “Voice Quality”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Nicotine” OR “Tobacco Use Disorder”) | |
| (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco”) | |
| (“Pulmonary Disease, Chronic Obstructive”) AND (“Dysphonia” OR “Vocal Cord Dysfunction”) AND (“Cigarette Smoking” OR “Smoking”) | |
| (“Pulmonary Disease, Chronic Obstructive”) AND (“Voice” OR “Phonation”) AND (“Nicotine” OR “Tobacco Smoking”) | |
| (“Dysphonia” OR “Voice Disorders”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Risk Factors”) AND (“Tobacco Use Disorder”) | |
| (“Vocal Cords” OR “Voice Quality”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco” OR “Tobacco Use Disorder”) | |
| (“Voice” OR “Voice Disorders”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco Smoking” OR “Tobacco Products”) | |
| (“Dysphonia”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Smoking” OR “Nicotine” OR “Tobacco Use Disorder”) | |
| (“Dysphonia”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco Smoking” OR “Tobacco”) | |
| (“Vocal Cord Dysfunction”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Cigarette Smoking” OR “Nicotine”) | |
| (“Pulmonary Disease, Chronic Obstructive”) AND (“Smoking” OR “Tobacco Smoking”) | |
| (“Vocal Cord Dysfunction”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco Smoking” OR “Tobacco”) | |
| (“Vocal Cord Dysfunction”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco Use Disorder” OR “Tobacco Products”) | |
| (“Pulmonary Disease, Chronic Obstructive”) AND (“Cigarette Smoking”) | |
| (“Voice”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Cigarette Smoking” OR “Tobacco”) | |
| (“Voice”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco Smoking” OR “Smoking”) | |
| PUBMED, SPRINGER LINK, SCIENCEDIRECT, SCOPUS, y EBSCO | (“Voice”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco Use Disorder” OR “Tobacco Products”) |
| (“Phonation”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Cigarette Smoking” OR “Smoking”) | |
| (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco Use Disorder”) | |
| (“Phonation”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Nicotine” OR “Tobacco” OR “Tobacco Use Disorder”) | |
| (“Vocal Cords”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Cigarette Smoking” OR “Tobacco Products”) | |
| (“Vocal Cords”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco Smoking” “Nicotine”) | |
| (“Pulmonary Disease, Chronic Obstructive”) AND (“Nicotine”) | |
| (“Voice Quality”) AND (“Risk Factors”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco Smoking” OR “Tobacco”) | |
| (“Vocal Cords”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco Use Disorder” OR “Smoking”) | |
| (“Pulmonary Disease, Chronic Obstructive”) AND (“Smoking” OR “Tobacco Products”) | |
| (“Voice Quality”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Cigarette Smoking” OR “Smoking” OR “Nicotine”) | |
| (“Voice Quality”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco Smoking” OR “Tobacco”) | |
| (“Voice Disorders”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Cigarette Smoking” OR “Smoking” OR “Tobacco Smoking”) | |
| (“Voice Disorders”) AND (“Pulmonary Disease, Chronic Obstructive”) AND (“Tobacco” OR “Nicotine” OR “Tobacco Use Disorder”) |
Source: own elaboration.
Characteristics of the Studies
Initially, we classified the studies that were characterized by including tobacco consumption in adults with COPD, additionally, articles where the characteristics and effects of tobacco consumption on the voice as a cause of Organic Dysphonia in adults with COPD were shown, it was taken into account that these studies had characteristics and aspects such as: adult population with COPD, smoking history, manifestations of the population with respect to vocal and respiratory problems or alterations and thus give development to the research topic.
Selection and Analysis
A preliminary selection of studies was considered, based on the established inclusion criteria, population characteristics, type of study and year. Subsequently, a registration table in Excel, prepared by the authors, was filled in independently, in which the key elements of each of the selected studies were specified. Following the structure proposed by the PRISMA statement, the process used in the identification, screening, eligibility and inclusion of articles is briefly described.
GRADE pro GDT was used through the clinical management question, including in the analysis number of studies, study design, risk of bias, inconsistency, indirect evidence, imprecision and the degree of certainty of the study (42).
RESULTS
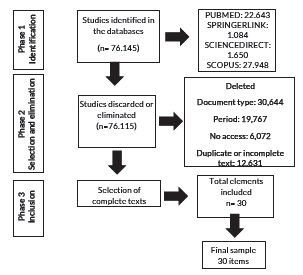
The eligibility criteria were determined following the order established in the methodology, through the developme t of each of the phases of the PRISMA flowchart (figure).
Identification Phase
The search was performed in the PUBMED, SPRINGER LINK, SCIENCEDIRECT, SCOPUS and EBSCO databases, according to the variable cross-references constructed from the DESC and MESH keywords. The following filters were then applied: document type, time window, full text or duplicate, and articles without access and non-compliance with criteria. Finally, articles were selected to obtain the final sample of 30 articles used in this research (see table 5).
Table 5 Filters Applied
| Database | Total articles | Type of document | Period | Incomplete and/or duplicate texts | No access | Noncompliance with criteria | Selected articles |
|---|---|---|---|---|---|---|---|
| PUBMED | 22.643 | 20.980 | 786 | 12 | 228 | 634 | 3 |
| SPRINGER LINK | 1.084 | 493 | 211 | 0 | 203 | 167 | 10 |
| SCIENCEDIRECT | 1.650 | 717 | 434 | 53 | 307 | 132 | 7 |
| SCOPUS | 27.948 | 7.652 | 7.863 | 3.875 | 3.871 | 4.679 | 8 |
| EBSCO | 22.820 | 802 | 10.473 | 2.132 | 8.022 | 1.389 | 2 |
| Total | 76.145 | 30.644 | 19.767 | 6.072 | 12.631 | 7.001 | 30 |
Source: own elaboration.
Selection and Elimination Phase
The initial selection of the research articles was made by preliminary reading of the titles, abstracts, and, later, the introduction, which allowed the identification of the most relevant articles with respect to the topic under investigation, with a total of 30 articles selected. The results of each variable cross-checking in English are listed below (see table 6) for the five databases PUBMED, SPRINGER LINK, SCIENCEDIRECT, SCOPUS, and EBSCO.
Table 6 Results of Cross-referencing Variables in English in the Databases
| Cruces | Data Base | ||||
|---|---|---|---|---|---|
| Pubmed | Springer Link | Sciencedirect | Scopus | Ebsco | |
| Pulmonary Disease, Chronic Obstructive + Cigarette Smoking | 1 | 0 | 1 | 0 | 0 |
| Pulmonary Disease, Chronic Obstructive + Nicotine | 1 | 0 | 1 | 1 | 0 |
| Pulmonary Disease, Chronic Obstructive + Tobacco Use Disorder | 1 | 0 | 0 | 1 | 0 |
| Pulmonary disease, chronic obstructive + Dysphonia + Tobacco | 0 | 1 | 0 | 0 | 0 |
| Cigarette Smoking + Voice Disorders + Voice Quality + Pulmonary Disease, Chronic Obstructive | 0 | 2 | 0 | 0 | 0 |
| Dysphonia + Vocal Cord Dysfunction + Voice Disorders + Pulmonary Disease, Chronic Obstructive + Tobacco Use Disorder + Smoking | 0 | 1 | 0 | 1 | 0 |
| Dysphonia + Pulmonary Disease, Chronic Obstructive + Cigarette Smoking | 0 | 1 | 0 | 0 | 0 |
| Vocal Cord Dysfunction + Phonation + Pulmonary Disease, Chronic Obstructive + Smoking + Tobacco Smoking | 0 | 1 | 1 | 1 | 0 |
| Voice + Voice Quality + Pulmonary Disease, Chronic Obstructive + Nicotine + Tobacco Use Disorder | 0 | 1 | 0 | 0 | 0 |
| Pulmonary Disease, Chronic Obstructive + Dysphonia + Vocal Cord Dysfunction + Cigarette Smoking + Smoking | 0 | 1 | 0 | 2 | 0 |
| Voice + Voice Disorders + Pulmonary Disease, Chronic Obstructive + Tobacco Smoking + Tobacco Products | 0 | 1 | 0 | 0 | 0 |
| Dysphonia +Pulmonary Disease, Chronic Obstructive + Tobacco Smoking + Tobacco | 0 | 1 | 0 | 0 | 0 |
| Pulmonary disease, chronic obstructive + Vocal Cord Dysfunction + Tobacco | 0 | 0 | 1 | 0 | 0 |
| Pulmonary disease, chronic obstructive + Dysphonia + Voice + Cigarette Smoking + Tobacco | 0 | 0 | 1 | 0 | 0 |
| Pulmonary disease, chronic obstructive + Phonation + Vocal Cords + Tobacco Smoking + Nicotine | 0 | 0 | 1 | 0 | 0 |
| Pulmonary disease, chronic obstructive + Voice Disorders + Voice + Smoking + Tobacco Use Disorder | 0 | 0 | 1 | 1 | 1 |
| Dysphonia + Pulmonary Disease, Chronic Obstructive + Smoking + Nicotine + Tobacco Use Disorder | 0 | 0 | 0 | 1 | 0 |
| Pulmonary Disease, Chronic Obstructive + Tobacco Use Disorder | 0 | 0 | 0 | 0 | 0 |
| Voice + Pulmonary Disease, Chronic Obstructive + Tobacco Smoking + Smoking | 0 | 0 | 0 | 0 | 1 |
| Total | 3 | 10 | 7 | 8 | 2 |
Source: own elaboration.
In the first search, 43 cross-references were made in English, among the different variables, resulting in 3 articles in PUBMED, 10 articles in SPRINGERLINK, 7 articles in SCIENCEDIRECT, 8 articles in SCOPUS and 2 articles in EBSCO, for a total of 30 articles.
Classification of the Quality of the Evidence
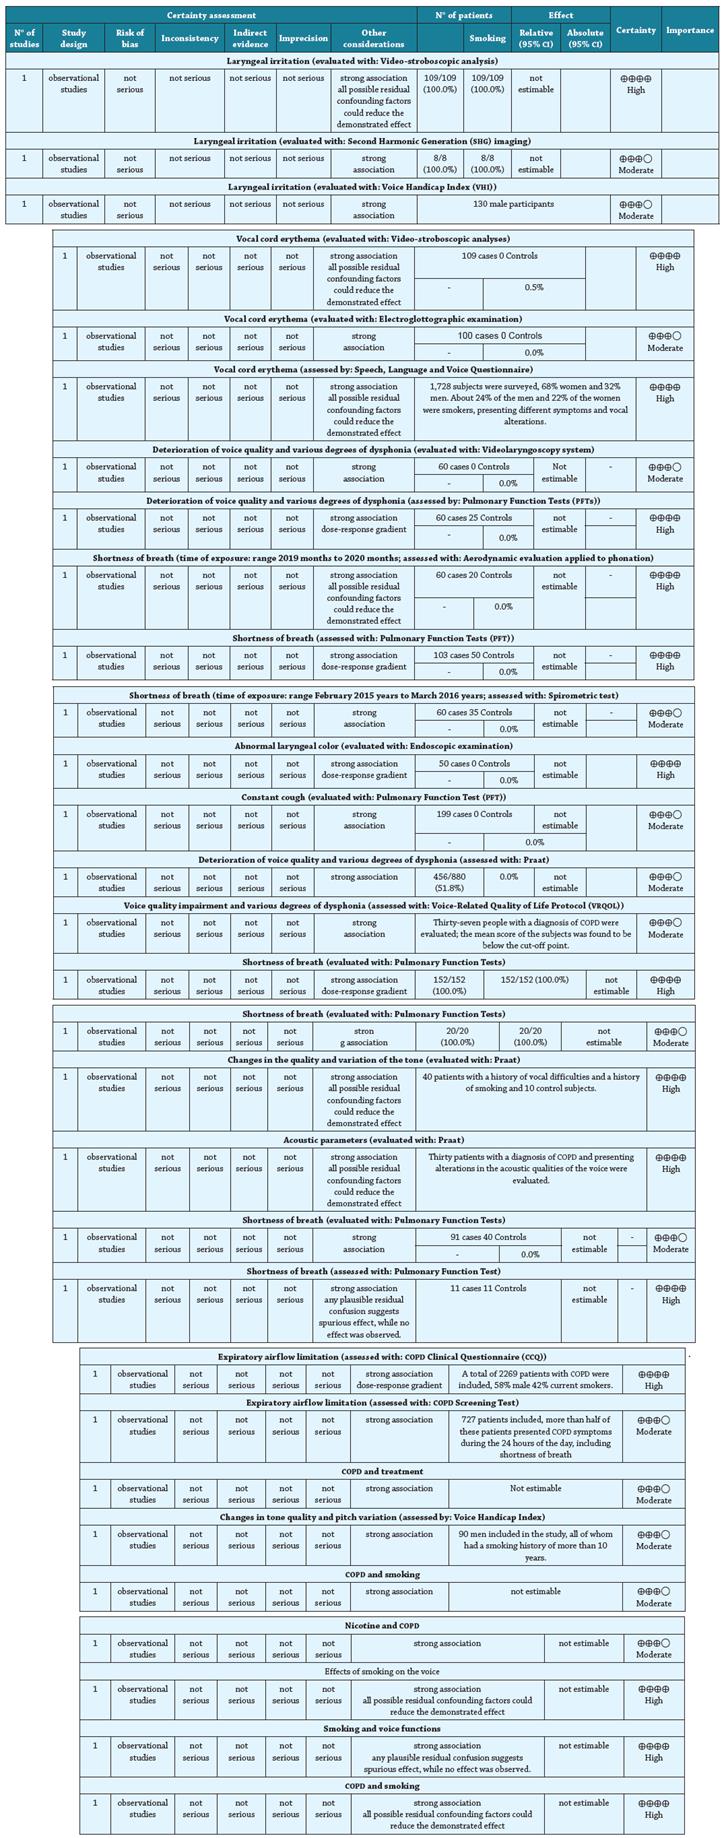
The classification of the quality of evidence and grading of the strength of recommendation was performed through the GRADE system, which was highly specialized for the scientific analysis of the studies included in this study. This resulted in a high level of moderate certainty (15 articles) and a high level of certainty (15 articles), thus demonstrating a high quality of evidence for each result and, in general, for the review carried out (see table 7).
Inclusion Phase
The selection was made after reading the titles and abstracts of the articles and they were analyzed in their entirety with a complete reading, applying criteria that allowed a selection, thus obtaining those that gave an answer to the question posed. The selection corresponded to a final sample of 30 articles (see table 8).
Table 8 Selection of Studies
| Nº | Database | Title | Author | Year | URL | Contribution |
|---|---|---|---|---|---|---|
| 1 | PUBMED | Pathogenesis of chronic obstructive pulmonary disease (COPD) induced by cigarette smoke | Mari Hikichi, Kenji Mizumura, Shuichiro Maruoka, Yasuhiro Gon | 2019 | (43) (Accessed May 12, 2023) | Tobacco smoke induces airway inflammation in COPD and affects vocal quality. |
| 2 | PUBMED | Implications of the Immune Landscape in COPD and Lung Cancer: Smoking Versus Other Causes | Elisabeth Taucher, Iurii Mykoliuk, Joerg Lindenmann and Freyja-Maria Smolle-Juettner | 2022 | (44) (Accessed May 12, 2023) | Respiratory infections such as COPD due to tobacco consumption, in turn causes laryngeal alterations. |
| 3 | PUBMED | Unravelling the many faces of COPD to optimize its care and outcomes | Patrick Mulhall and Gerard Criner | 2016 | (45) (Accessed May 12, 2023) | Progressive and irreversible narrowing of the airways mainly due to smoking. |
| 4 | SPRINGER LINK | Study of voice disorders in patients with bronchial asthma and chronic obstructive pulmonary disease | Adel M. Saeeda, Nermine M. Riada, Nehad M. Osmana Ahmed Nabil Khattabb, Shymaa E. Mohammeda | 2018 | (16) (Accessed May 15, 2023) | COPD causes adverse effects on the voice; all patients with COPD had dysphonia as the main cause of tobacco consumption. |
| 5 | SPRINGER LINK | Voice changes in patients with chronic obstructive pulmonary disease | Enas Elsayed Mohamed a, Riham Ali El maghraby | 2014 | (17) (Accessed May 15, 2023) | Many COPD patients experience voice changes; dysphonia was perceived in 50% of them. |
| 6 | SPRINGER LINK | The Utility of Pulmonary Function Testing in Patients Presenting with Dysphonia | Kirsten Meenan, Lisa Catanoso, Julien Aoyama, Stephen R. Stephan, Ridley Chauvin, and Robert T. Sataloff | 2019 | (11) (Accessed May 15, 2023) | In COPD, the voice can be affected by the symptoms of the disease, leading to a breathy voice quality. |
| 7 | SPRINGER LINK | Investigating the Effects of Smoking on Young Adult Male Voice by Using Multidimensional Methods | Dogan Pinar, Hakan Cincik, Evren Erkul, and Atila Gungor, Istanbul, Turkey | 2015 | (12) (Consulted on May 16, 2023) | Tobacco smoking causes edema and erythema of the vocal cords, impairing the vibratory function of the vocal cords and is the main factor in COPD. |
| 8 | SPRINGER LINK | Enfermedad Pulmonar Obstructiva Crónica y Tabaquismo | Francisco Arancibia H. | 2017 | (13) (Accessed May 16, 2023) | The main risk factor for COPD is smoking, causing respiratory and vocal alterations. |
| SPRINGER LINK | Evaluating the efects of smoking on the voice and subjective voice problems using a meta- analysis approach | Haewon Byeon & Seulki Cha | 2020 | (6) (Accessed May 16, 2023) | Smoking tobacco irritates and dries the mucosa of the vocal cords, causing laryngitis and Reinke’s edema. | |
| 10 | SPRINGER LINK | Objective and Subjective Evaluation of Larynx in Smokers and Nonsmokers: A Comparative Study | Hansa Banjara, Varsha Mungutwar, Digvijay Singh and Anuj Gupta | 2014 | (4) (Accessed May 16, 2023) | Tobacco smoking causes laryngeal alterations in the epithelium of the vocal cords, affecting the acoustic properties of the voice. |
| 11 | SPRINGER LINK | Collagen Microstructure in the Vocal Ligament: Initial Results on the Potential Effects of Smoking | Jordan E. Kelleher, PhD; Thomas Siegmund, PhD; Roger W. Chan, PhD | 2014 | (46) (Accessed May 17, 2023) | Tobacco smoking causes chronic irritation and increased vocal cord mass, in addition to affecting the acoustic properties of the voice. |
| 12 | SPRINGER LINK | Influence of smoking isolated and associated to multifactorial aspects in vocal acoustic parameters | Aline Gomes Lustosa Pintoa, Agrício Nubiato Crespob, Lucia Figueiredo Mourão | 2014 | (1) (Consulted on May 17, 2023) | In addition to affecting the voice, smoking triggers pulmonary difficulties such as COPD. |
| 13 | SPRINGER LINK | Multimodal Analysis of Dysphonia in Smokers: A Two-Year Comprehensive Study | Neha Raghuwanshi, Aparaajita Mundra, Neeraj Kumar Dubey, Surbhi Godha, Rajkumar Mundra | 2021 | (47) (Accessed May 17, 2023) | Observable effects of smoking on vocal cord microanatomy, chief complaint dysphonia in tobacco smokers. |
| 14 | SCIENCE DIRECT | Towards the Objective Speech Assessment of Smoking Status based on Voice Features: A Review of the Literature | Zhizhong Ma, Chris Bullen, Joanna Ting Wai Chu, Ruili Wang, Yingchun Wang, and Satwinder Singh, y Auckland. | 2023 | (48) (Accessed May 17, 2023) | Smoking causes inflammation and malfunction of the vocal cords and affects the acoustic properties of the vocal cord. |
| 15 | SCIENCE DIRECT | Quality of Life Predictors in Voice of Individuals with Chronic Obstructive Pulmonary Disease | Gabriele dos Anjos Palagi da Silva, Thais Dias Feltrin, Fernanda dos Santos Pichini, Carla Aparecida Cielo, and Adriane Schmidt Pasqualoto, Santa Maria, and y Curitiba. | 2022 | (9) (Consulted on May 18, 2023) | People with COPD may present signs and symptoms such as vocal alterations due to respiratory and muscular damage. |
| 16 | SCIENCE DIRECT | Multiple symptoms, functioning, and general health perception in people with severe COPD over time | Soo Kyung Park, PhD, RN a, Janet L. Larson, PhD, RN | 2016 | (49) (Accessed May 18, 2023) | People with COPD present vocal discomfort and its main etiology is tobacco consumption. |
| 17 | SCIENCE DIRECT | Goals of COPD treatment: Focus on symptoms and exacerbations | Claus F. Vogelmeier a, Miguel Roman- Rodríguez b, Dave Singh c, MeiLan K. Han d, Roberto Rodríguez-Roisin, Gary T. Ferguson | 2020 | (21) (Accessed May 18, 2023) | Smoking causes COPD and its symptoms include vocal alterations. |
| 18 | SCIENCE DIRECT | Gender Differences in the Prevalence of Vocal Symptoms in Smokers | Susanna Simberg, Hanna Udd, and Pekka Santtila, Abo | 2015 | (50) (Accessed May 18, 2023) | Smoking tobacco causes vocal and respiratory alterations. |
| 19 | SCIENCE DIRECT | The Effect of Smoking on the Fundamental Frequency of the Speaking Voice | Marie Reine Ayoub, Pauline Larrouy-Maestri, and Dominique Morsomme, Li ege, Belgium, and y Frankfurt. | 2019 | (51) (Accessed May 18, 2023) | Tobacco smoking significantly affects the vocal apparatus; tobacco smokers report vocal complaints. |
| 20 | SCIENCE DIRECT | Using Receiver Operating Characteristic Curve to Define the Cutoff Points of Voice Handicap Index Applied to Young Adult Male Smokers | Dionysios Tafiadis, Spyridon K. Chronopoulos, Evangelia I. Kosma, Louiza Voniati, Vasilis Raptis, Vasiliki Siafaka, and Nausica Ziavra, Ioannina, Arta, and Larissa, Greece, and Nicosia. | 2018 | (52) (Accessed May 18, 2023) | Smoking causes changes in the larynx and alterations in the voice mechanism, as well as respiratory and pulmonary problems. |
| 21 | SCOPUS | Is insufficient pulmonary air support the cause of dysphonia in chronic obstructive pulmonary disease? | Megahed M. Hassan a, Mona T. Hussein b, Ahmed Mamdouh Emam a Usama M. Rashad c, Ibrahim Rezk c, Al Hussein Awad | 2018 | (14) (Accessed May 19, 2023) | Tobacco smokers have a high prevalence of dysphonia, COPD may include vocal abnormalities. |
| 22 | SCOPUS | Respiratory Symptoms Items from the COPD Assessment Test Identify Ever-Smokers with Preserved Lung Function at Higher Risk for Poor Respiratory Outcomes | Martinez, C. H., Murray, S., Barr, R. G., Bleecker, E., Bowler, R. P., Christenson, S. A | 2017 | (53) (Accessed May 19, 2023) | Tobacco smokers present respiratory and pulmonary alterations, as well as vocal difficulties. |
| 23 | SCOPUS | Distinguishing between pre- and post-treatment in the speech of patients with chronic obstructive pulmonary disease | Andreas Triantafyllopoulos, Markus Fendler, Anton Batliner, Maurice Gerczuk, Shahin Amiriparian, Thomas M. Berghaus and Bjorn W. Schuller | 2022 | (54) (Accessed May 19, 2023) | The predominant cause of the voice is tobacco consumption and this affects the voice significantly. |
| 24 | SCOPUS | Speech-Based Support System to Supervise Chronic Obstructive Pulmonary Disease Patient Status | Mireia Farrús, Joan Codina-Filbà, Elisenda Reixach, Erik Andrés, Mireia Sans, Noemí Garcia 4 and Josep Vilaseca | 2021 | (55) (Accessed May 19, 2023) | COPD patients suffer voice changes, tobacco consumption influences voice quality alterations. |
| 25 | SCOPUS | Analysis of Acoustic Parameters from Respiratory Signal in COPD and Pneumonia patients | Neili Zakaria Fezari, Mohamed Abdeghani, Redjati | 2019 | (56) (Accessed May 20, 2023) | COPD is caused by tobacco use and affects the respiratory signal and phonation. |
| 26 | SCOPUS | Assessment of Chronic Pulmonary Disease Patients Using Biomarkers from Natural Speech Recorded by Mobile Devices | Viswam Nathan, Korosh Vatanparvar, Md Mahbubur Rahman, Ebrahim Nemati, Jilong Kuang | 2019 | (57) (Accessed May 20, 2023) | Lung conditions such as COPD affect voice production and speech patterns. |
| 27 | SCOPUS | Morning and night symptoms in primary care COPD patients: a cross-sectional and longitudinal study. An UNLOCK study from the IPCRG | Ioanna Tsiligianni, Esther Metting, Thys van der Molen, Niels Chavannes and Janwillem Kocks | 2016 | (58) (Accessed May 20, 2023) | Tobacco smokers present poor pulmonary function, with a hoarse voice and constant throat clearing. |
| 28 | SCOPUS | Observational study to characterise 24-hour COPD symptoms and their relationship with patient-reported outcomes: results from the ASSESS study | Marc Miravitlles, Heinrich Worth, Juan José Soler Cataluña, David Price, Fernando De Benedetto, Nicolas Roche, Nina Skavlan Godtfredsen, Thys van der Molen, Claes-Göran Löfdahl, Laura Padullés and Anna Ribera | 2014 | (59) (Accessed May 20, 2023) | Among the characteristic symptoms of COPD are respiratory and vocal disturbances. |
| 29 | EBSCO | Self-Perceived Handicap Associated With Dysphonia and Health- Related Quality of Life of Asthma and Chronic Obstructive Pulmonary Disease Patients: A Case-Control Study | Rafael Hurtado- Ruzza, a, Óscar Álvarez-Calderón Iglesias, Ricardo Becerro-de-Bengoa- Vallejo, C César Calvo- Lobo,c Marta San-Antolín,d Marta Elena Losa- Iglesias,e Carlos Romero-Morales,f and Daniel López-Lópeza | 2021 | (7) (Accessed May 20, 2023) | People with COPD show higher prevalence of dysphonia and higher levels of vocal fatigue, contributing to changes in vocal quality and pitch variation. |
| 30 | EBSCO | Role of Genetic Susceptibility in Nicotine Addiction and Chronic Obstructive Pulmonary Disease | Gloria Pérez- Rubio1, Elizabeth Córdoba-Lanús, Paula Cupertino, Francisco Cartujano-Barrera, Michael A. Campos4 and Ramcés Falfán-Valencia | 2019 | (2) (Accessed on May 20, 2023) | All tobacco smokers develop some level of lung inflammation, but in people with COPD, the inflammation is denser and damaging. |
Source: own elaboration.
Table 9 shows the effects caused and structures affected corresponding to Organic Dysphonia produced by tobacco consumption in adults with COPD.
Table 9 Effects and Structures Affected in Organic Dysphonia Caused by Smoking in Adults with COPD
| Effect | Structure |
|---|---|
| O Enlarged laryngeal mucosa 7 16 51 O Acute laryngitis caused by an infection of the upper respiratory tract 17 11 6 O Cancer of the larynx 17 12 50 O Laryngeal irritation 12 4 46 52 O Smoking produces anatomical changes in the larynx 6 O Laryngospasm 1 O Abnormal laryngeal color 50 O Benign and malignant tumors 52 | Larynx |
| O Incomplete adduction of the vocal folds 7 O Diffuse congestion, unhealthy mucosa and edema of the vocal folds 16 4 O Bilateral edema of the vocal folds 16 O Reinke’s edema 17 6 50 52 O Increase of the vascularization of the vocal cords 16 -Nódulos en las cuerdas vocales 11 58 O Vocal cord polyps 11 47 O Vocal cord erythema 12 4 50 O Abnormal edge of the vocal cords 4 4 | Vocal cords |
| O Tos constant 7 16 17 11 2 6 1 9 | Lungs |
| O Glottic edema due to smoking 16 | Glotis |
| O Inflammation, irritation and dryness 14 6 | Vocal tract |
| O Thickening, aberrations and carcinomas 46 | Epithelium of the Vocal Cords |
| O Idiopathic subglottic stenosis 1 | Subglottis |
| O Chest tightness 7 59 O Pulmonary disorders 17 13 9 O Decreased pulmonary function 11 O Smoking leads to lung disease, which can cause dysphonia 11 O Expectoration 2 6 (1) 59 O Pulmonary hypersecretion 9 O Lung cancer 44 | Lungs |
| O Inflammation of the respiratory tract 7 43 51 O Progressive and irreversible narrowing of the airways 45 | Respiratory tract |
Source: own elaboration.
Table 10 Effects and Affected Functions in Organic Dysphonia Caused by Tobacco use in Adults with COPD
| Effect | Function |
|---|---|
| O Vocal fatigue 7 O Strained voice 16 14 14 21 50 O Slurred voice 16 O Clearing 44 1 1 52 O Vocal alterations due to smoking 17 9 9 O Increased mucus production, leading to a clipped or raspy voice quality 11 O Vocal weakness and aphonia 11 O Deterioration of voice quality and various degrees of dysphonia 16 11 14 O Hoarseness 46 1 47 | Voice |
| O Prosodic characteristics 55 57 | Speak to |
| O Laryngeal hypersensitivity 7 | Hypersensitivity |
| O Changes in the quality and variation of the tone 7 16 1 9 | Quality and tone of voice |
| O Insufficient glottic closure leading to a decrease in the duration of phonation time 7 6 4 50 | Maximum Phonation Time |
| O Decrease of the fundamental frequency 6 4 46 48 57 50 51 O Jitter variation 6 4 4 57 51 | Fundamental frequency |
| O Variation of shimmer 6 4 57 | Voice amplitude |
| O Harmonic Noise Ratio (HNR) impairment 4 48 | Harmonic |
| O Altered phonatory physiology 12 4 46 52 | Phonation |
| O Limitation of respiratory support which causes difficulties in speech and loss of speech volume 17 O Wheezing 2 49 49 57 58 59 O Respiratory infections 21 O Difficulty in breathing 7 11 17 2 9 49 21 59 7 11 17 2 9 49 21 59 -Limited expiratory airflow 7 54 53 O Shortness of breath 7 11 11 17 2 9 49 21 59 | Breathing |
Source: own elaboration.
ANALYSIS AND DISCUSSION
Smoking is the leading cause of preventable death worldwide, and it is considered a public health problem. Tobacco smoke is made up of different toxic and carcinogenic compounds, including nicotine, nitrogen oxides and carbon monoxide 9.
Once nicotine is inhaled, it is absorbed and transmitted to the brain, where it acts on specialized receptors that cause the release of neurotransmitters, especially dopamine. The pleasurable effects of this neurotransmitter result in positive feedback that leads to addiction. 45 Continuing to smoke tobacco produces neuroadaptive tolerance, while quitting causes withdrawal symptoms, as well as irritability, anxiety and depression; in addition, the conditioned behaviors, i.e., the pleasure after a meal, developed by a smoker over the year serve as reinforcement to continue smoking tobacco. 45
Smoking is also an important factor that has a deleterious effect on vocal health 9, and it is considered one of the main causes of vocal disorders, 50 likewise, according to the International Union Against Cancer, tobacco smoking is considered the most important risk factor in the etiology of laryngeal cancer 12.
Changes in the anatomical structure of the larynx can cause functional problems and as a result, can adversely affect voice production and lead to voice disorders. 6 From a clinical/acoustic voice perspective, tobacco smoking has been shown to induce acoustic changes in characteristics such as fundamental frequency (FO), jitter, shimmer, harmonic-to-noise ratio (HNR), 48,57,7) brightness, maximum phonation time, pitch variation and sound quality, tense voice, throat clearing, changes in pitch quality and pitch variation, deterioration of voice quality and various degrees of dysphonia, 16,6,4 increased mucus production, leading to a choppy or raspy voice quality, vocal weakness and aphonia, 11,21 resulting in impaired oral communication.
It is widely known that voice disorders have a very high recurrence rate worldwide. Particularly, even if voice rehabilitation is performed after the onset of a disorder or disturbance, the risk of recurrence is even higher unless the risk factor that adversely affects it and causes its etiology is eliminated 6.
Regarding the structure of the vocal folds, it is stated that smoking tobacco causes chronic irritation and abnormal texture 46, edema, mainly in the superficial layers, presence of erythema, nodules and polyps in the vocal folds, 11,47 abnormalities in flexibility or stiffness, abnormalities of the size of the glottic space, resulting in microscopic alterations identified in the epithelium, and abnormal and swollen border 4, as well as Rheinke's edema, leukoplakia, glottic edema, abnormalities in flexibility or stiffness due to prolonged edema, increased vascularization of the vocal folds 16,46, inflammation, irritation and dryness in the vocal tract, 14,6 enlarged laryngeal mucosa, incomplete adduction of the vocal folds, 7 thickening, aberrations and carcinomas in the vocal fold epithelium, 46 acute laryngitis caused by an upper respiratory tract infection, laryngeal cancer, 17,11,12,6 likewise, tobacco favors the increase in the production of cells and change in the shape of the vocal folds, contributing to the appearance of vocal fold cancer. 1
Prolonged exposure of the laryngeal mucosa to tobacco compromises its mucoondulatory movement, chronic inflammation or irritation, benign and malignant tumors, 52 mucosal edema or interaritenoid thickening and modifies voice quality causing burning sensation, throat clearing and presence of secretions and laryngitis. 1 Likewise, a relationship between tobacco smoke exposure and different types of cancer, respiratory, cardiovascular, infectious and neurological diseases has been demonstrated 44.
Since voice production results from complex interactions between the respiratory and phonatory systems, tobacco smoking can result in a much more drastic loss of pulmonary function and dysphonia 17, which is characterized by respiratory as well as systemic and extrapulmonary manifestations that may be accompanied by various comorbidities such as heart failure, cardiac arrhythmias, anemia, weight loss, anxiety, depression, diabetes, increased muscle pain, wheezing, frequent coughing. 13
In addition to typical pulmonary symptoms such as dyspnea, increased mucus production, cough and decreased exercise capacity, in COPD, the voice can be affected by various symptoms of the disease, leading to diminished and choppy voice quality further affecting an individual's quality of life. 11,2 According to the American Speech-Language-Hearing Association, these and other symptoms of COPD can wreak havoc on the larynx and vocal cords, causing problems such as voice and communication disorders 17.
COPD can affect voice quality and production, both directly, associated with respiratory impairment, and indirectly, as a side effect of medication and associated with concurrent symptoms, contributing to dysphonia. 16 Similarly, individuals show limited ventilatory capacity and respiratory infections 21,58,59,43,51 with the consequent increase in respiratory frequency, which can compromise communication and decrease the Maximum Phonation Time, 49 causing COPD subjects to need numerous air refills to maintain and finish the sentence during conversation 9.
This being the case, pulmonary disorders cause limitation of vital capacity, which in turn will limit the respiratory support and control needed to speak effectively. 54 Adequate prevention of controllable diseases such as COPD through early smoking cessation and early intervention for patients who develop these diseases will play an important role in maintaining vocal strength and efficiency 17. Dysphonia can be directly related to alterations in airflow volume and velocity, so the decreased lung volume associated with COPD 55 and common dyspnea contribute to dysphonia and reduce message duration, resulting in decreased vocalization efficiency 17.
In contrast to other controversial interventions for the treatment of COPD, tobacco smoking cessation may be the most effective therapeutic intervention. It has been estimated that nearly one in five deaths can be attributed to the effects of smoking, and smoking remains the greatest risk factor for developing COPD. Quitting tobacco smoking is difficult, both, because of the addictive properties of nicotine, and the psychological dependence it causes 45.
CONCLUSIONS
Dysphonia is a common finding in adults with COPD, smoking being the main cause of their appearance.
Smoking affects the larynx and vocal cords causing notable alterations, such as irritation and enlargement of the laryngeal mucosa, benign and malignant tumors, increased vascularization, inflammation and dryness, edema, nodules, polyps and erythema in the vocal cords. Each of these manifestations affects not only the structures involved in the voice process, but also the acoustic characteristics of the voice, causing changes in tone quality and pitch variation, deterioration of voice quality, and various degrees of dysphonia.
Similarly, COPD can affect the quality and production of the voice, associated with respiratory impairment, these people may present difficulties in the voice, since phonation requires considerable respiratory capacity and as one of the main symptoms of COPD is the limitation and obstruction of expiratory airflow, leading to an imbalance between breathing and phonation, as well as decreased lung volume and dyspnea, contributing to dysphonia and reduce the duration of the message, resulting in a decrease in the efficiency of vocalization.

